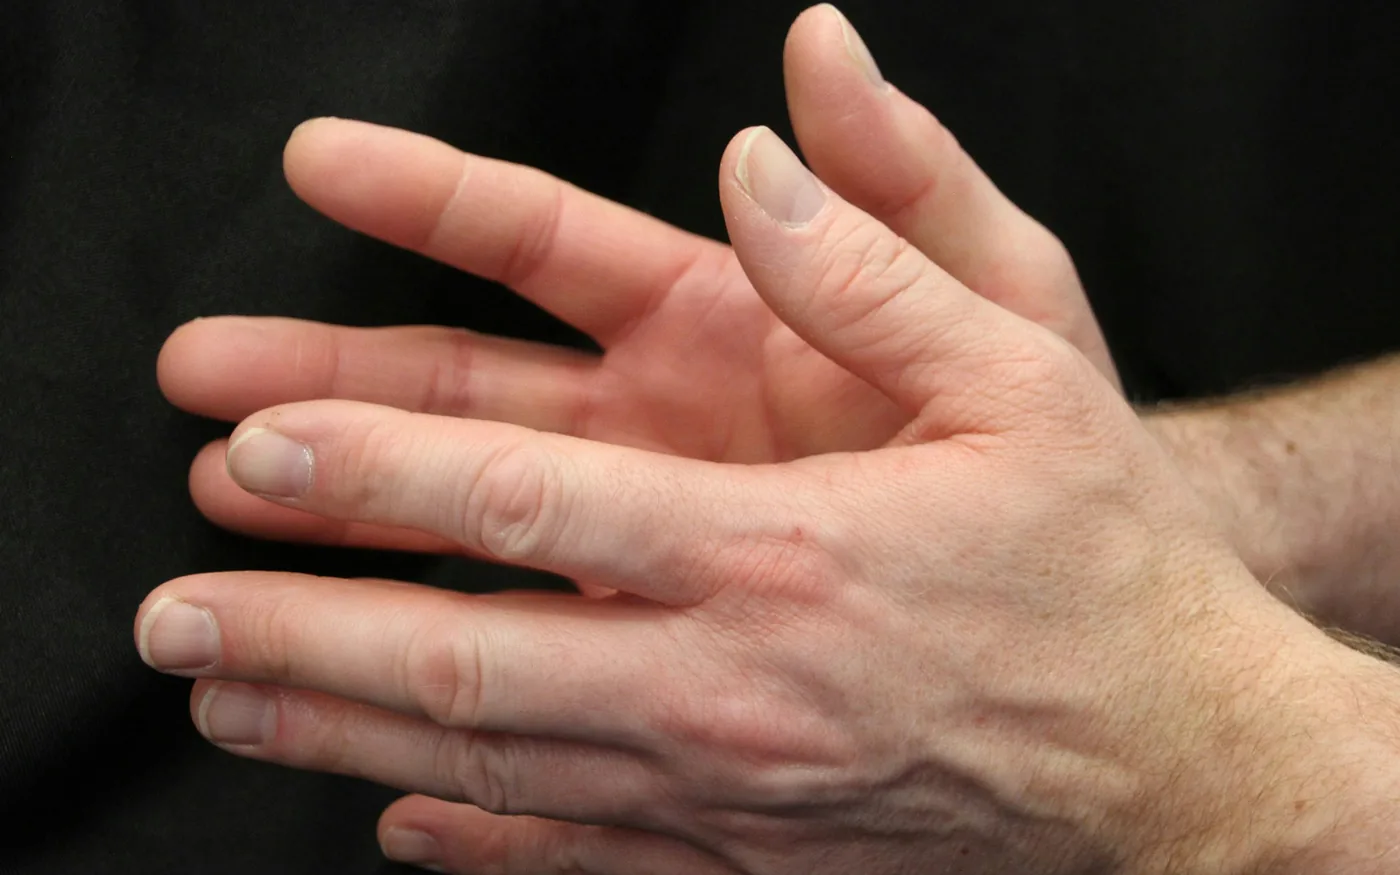
Two tendons run along the thumb side of the wrist inside a narrow sheath. Ask them to do something new and repetitive and the sheath becomes irritated, at which point every lift, grip and wring hurts in one very specific spot.
It is common, it is treatable, and it is constantly mistaken for arthritis.

The test you can do sitting there
Few conditions have a self-test this useful, so it is worth doing before reading further.
Tuck your thumb into your palm, close your fingers over it to make a fist, then tip the wrist downwards towards the little finger side. If that produces sharp pain over the bump on the thumb side of the wrist, that is a strongly suggestive finding.
A general ache, or pain somewhere else entirely, points elsewhere — which is the next section.

Not thumb arthritis, and not carpal tunnel
| De Quervain’s | Thumb base arthritis | Carpal tunnel | |
|---|---|---|---|
| Where | Thumb side of the wrist | At the thumb joint, towards the palm | Palm and fingers |
| Feels like | Sharp on movement | Deep ache on gripping | Tingling and numbness |
| Worst when | Lifting, wringing, thumb out | Pinching, jar lids, keys | At night |
| Swelling | Over the tendon sheath | Firm and bony | None visible |
| Numbness | No | No | Yes, thumb to ring finger |
| First line | Splint and change the movement | Orthosis and joint protection | Night splint and assessment |
Where it comes from
The history is usually more informative than the examination here, because the provoking activity is nearly always identifiable once you look for it.
Almost always a new or increased repetitive demand on the thumb, held out to the side while the wrist moves.
- Lifting a baby under the arms with thumbs out, many times a day. Easily the commonest presentation.
- A new job or task involving gripping, unscrewing, or repetitive thumb movement.
- Racquet sports and golf, particularly after a grip change.
- Phone and tablet use, which is a growing contributor and the one people are most reluctant to accept.
- Gardening seasons, where three months of nothing becomes six hours of pruning.

What actually helps
In order, and the first two do most of the work.
| Measure | What it does | Notes |
|---|---|---|
| Change the movement | Removes the provoking load | Scoop a baby from underneath with forearms, thumbs tucked |
| Thumb spica splint | Rests the two tendons | Leaves the fingers free to work |
| Ice over the area | Eases the local pain | Ten minutes, not longer |
| Anti-inflammatories | Reduce pain and swelling | Ask your pharmacist or doctor |
| Corticosteroid injection | Good evidence for stubborn cases | A medical conversation |
| Surgery | Releases the sheath | Rarely needed, and rarely first |
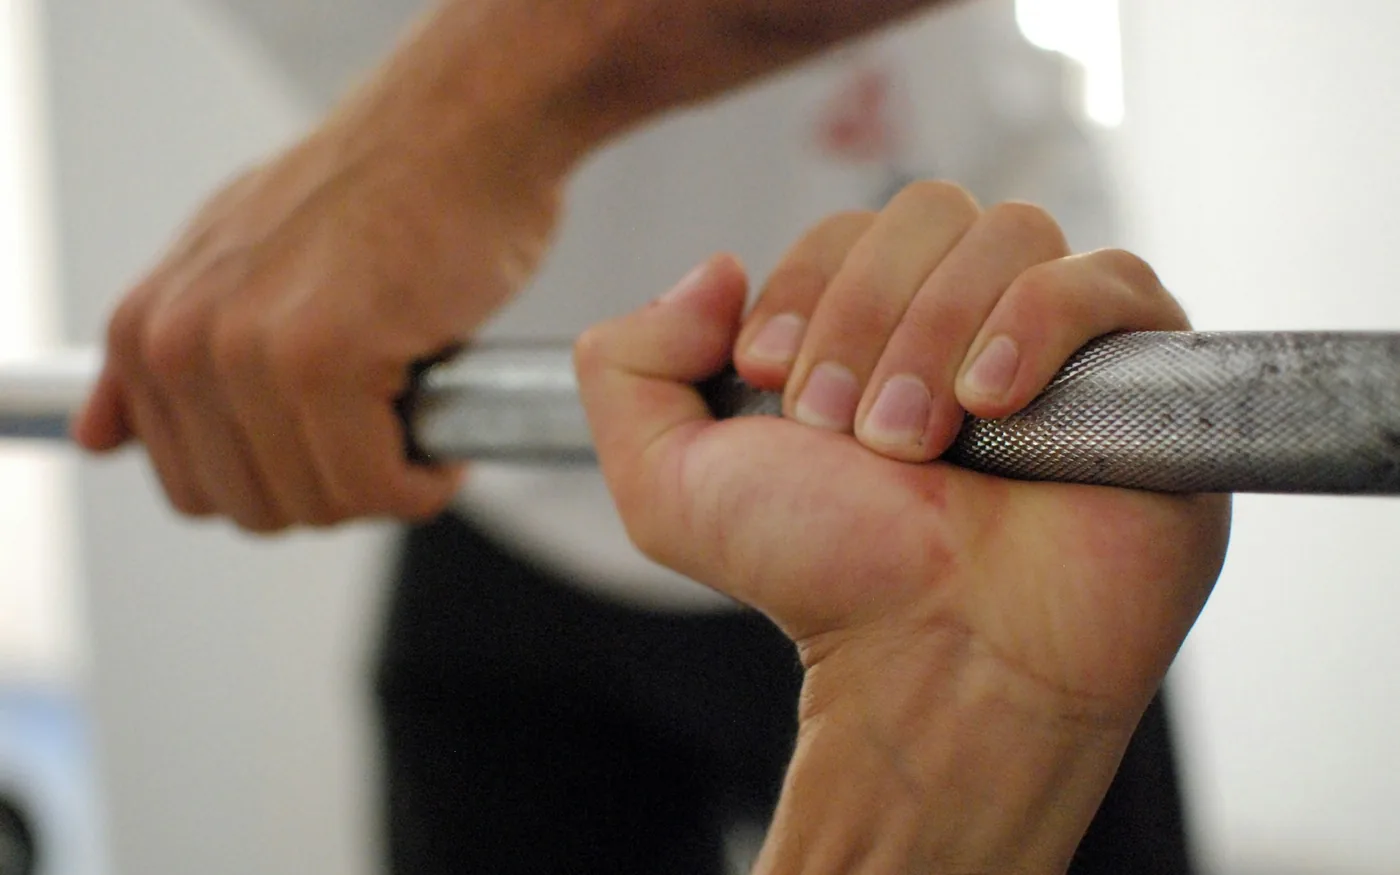
How long it takes
Longer than people hope, and the timeline depends almost entirely on whether the provoking movement actually stopped.
A case caught early, with a splint and a genuine change of technique, often settles in four to six weeks. A case that has been going for months while the same lifting continued can take considerably longer, and is the group most likely to end up discussing an injection.
Postpartum cases have their own pattern — many improve as the baby gets heavier and the lifting technique changes out of necessity, which is a slightly backhanded form of good news. UW Health publishes patient guidance on hand and wrist tendon problems if you want to read further.
The splint question
A thumb spica splint holds the thumb and wrist still while leaving the other fingers usable, which is what makes it tolerable for the people who most need it.
Worn during provoking activities and overnight is the usual pattern rather than continuously. As with arthritis at the base of the thumb, the aim is unloading the structure at the moments that hurt it, not immobilising a hand you need.

Where acupuncture and massage fit
As an adjunct. There is no strong condition-specific trial evidence for acupuncture in de Quervain’s and we are not going to invent any.
What treatment can reasonably do is ease the pain and the forearm tightness that builds around a guarded wrist, which makes the weeks more comfortable while the load management does the actual work. The reasoning is the same one set out in Achilles tendinopathy and shin splints.

One small practical note: whatever you change, change it for both hands. People who protect one wrist reliably overload the other, and then have two problems.
When to see a doctor
See a doctor for numbness or tingling in the hand, which points elsewhere; for a wrist that is hot, red or swollen with fever; for pain after a fall onto the hand, which needs a fracture excluded; or for pain that has not improved after six weeks of a splint and genuine activity change.
Booking a session in Beverly
Acupuncture is $75 a session and massage is $45 for 30 minutes, $75 for 60 and $105 for 90 — all on our rates page.
If the pain is on the other side of the wrist entirely, ulnar-sided wrist pain covers it — different structure, different provoking movements.
See also carpal tunnel syndrome, hand and thumb arthritis and tennis elbow, browse all our articles, or get in touch.
Frequently asked questions
Where exactly does de Quervain’s hurt?
On the thumb side of the wrist, roughly where a watch strap would sit, over the bony bump at the base of the thumb side of the forearm. Not at the thumb joint itself, which is further down towards the palm and points at arthritis instead.
What is the test I can do at home?
Tuck your thumb into your palm, close your fingers over it, then tip your wrist down towards your little finger. Sharp pain over that thumb-side bump is a strongly suggestive finding. It is called the Finkelstein test.
Why do new parents get it?
Lifting a baby repeatedly with the thumbs held out to the side loads exactly these two tendons, dozens of times a day, at a point when the body is already changing. Changing the lifting technique often matters more than any treatment.
Will a splint help?
Usually yes. A thumb spica splint rests the two tendons while leaving the fingers free. It is one of the standard first-line measures, and it works best combined with changing whatever movement is provoking it.
Does it need an injection?
Sometimes. Corticosteroid injection into the tendon sheath has good evidence for de Quervain’s and is often what settles a stubborn case. That is a conversation with your doctor, and it sits after the splint and the activity change rather than instead.
This article is general information, not medical advice. Acupuncture is intended to work alongside the care of your doctor, not to replace it. Please speak to a clinician about any new, severe or changing symptom.