Arm symptoms are one of the harder things to place, because four quite different problems produce a similar complaint and people usually get told about three of them.
This is the fourth, and it is the one where the trouble is happening well above the arm that hurts.

The four-way differential
| Where | Worst with | The giveaway | |
|---|---|---|---|
| Thoracic outlet | Whole arm, often the little finger side | Arms overhead, carrying | Elevation reproduces it |
| Carpal tunnel | Thumb to ring finger | At night | The little finger is spared |
| Pinched nerve in the neck | Neck to arm, named fingers | Neck movement | Hand on head eases it |
| Ulnar nerve at the elbow | Ring and little finger | Elbow bent, at night | Tapping the funny bone reproduces it — see golfer’s elbow |
| Vascular thoracic outlet | Whole arm, swollen or discoloured | Anything | Urgent assessment |
What is being compressed
The anatomy is worth a moment, because it explains why arm elevation is the test.
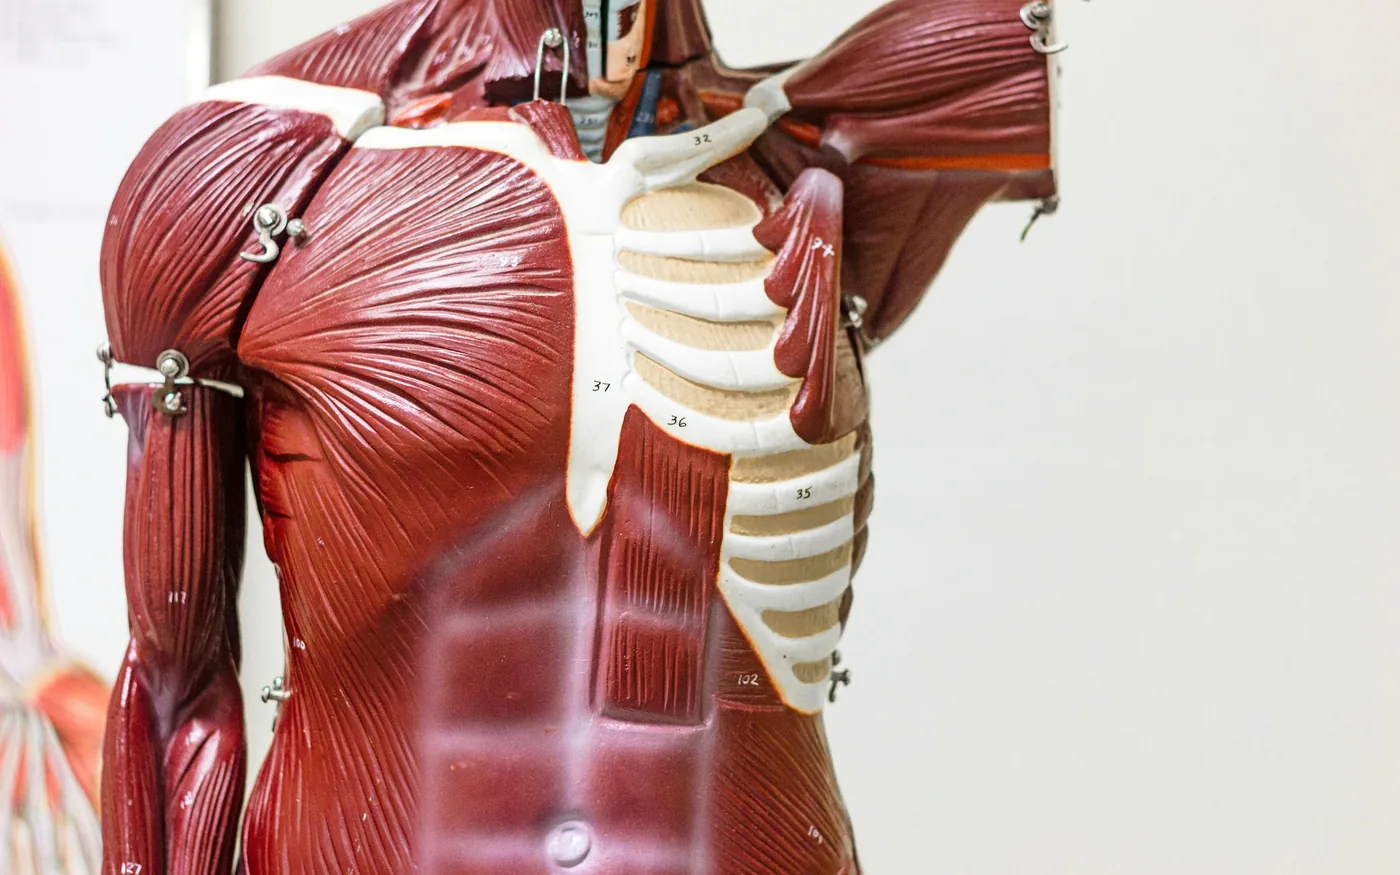
The nerves and blood vessels supplying the arm pass through a narrow corridor between the collarbone and the first rib, threading between two neck muscles on the way.
Anything that narrows that corridor — a slumped shoulder position held for hours, overdeveloped or overworked neck muscles, an extra rib present from birth, or an old collarbone fracture — can irritate what passes through it.
The urgent version
Short, and worth reading before anything else on this page.
The great majority of cases involve nerves and are a nuisance rather than a danger. A small minority involve the vein or the artery, and those behave differently.
Sudden swelling of one arm, with a bluish or mottled colour and a feeling of fullness, needs urgent assessment. It can indicate a clot in the vein at the outlet, and it is time-critical. Coldness, pallor or a weak pulse in one arm is the arterial equivalent and equally urgent.
The Society for Vascular Surgery publishes patient material on the vascular forms if you want the fuller picture.

Who tends to get it
Three patterns come up repeatedly, and two of them are occupational.
- Overhead work — painters, electricians, hairdressers, anyone whose arms spend hours above shoulder height.
- Carrying on one side, whether a bag, a toolbox or a small child.
- Swimmers and throwers, where repeated elevation is the sport rather than the job.
- After a collarbone fracture, where the healed bone can narrow the space.
- An extra rib present from birth, which is uncommon and usually only matters alongside the above.
A contested diagnosis, honestly
Neurogenic thoracic outlet syndrome has no gold-standard test. The provocative manoeuvres used to check for it — raising the arms, turning the head, feeling for a pulse change — produce positive results in plenty of people without symptoms.
So it is reached by fitting the picture together and excluding the alternatives, in the same way as piriformis syndrome. That is a reason for care rather than dismissal, and a reason to be wary of anyone who diagnoses it very quickly.
What actually helps
| Measure | Why | Note |
|---|---|---|
| Shoulder blade strengthening | Improves the position of the collarbone | The core of conservative treatment |
| Reducing overhead work | Removes the provoking position | Where the job allows |
| Both straps on the backpack | Halves the load on one shoulder | Free, immediate |
| Breathing pattern work | Overusing neck muscles to breathe tightens the outlet | More useful than it sounds |
| Nerve gliding | Gentle mobility for the nerve itself | Gently — forcing it provokes |
| Surgery | For vascular forms and refractory nerve cases | After proper rehabilitation, not before |

The breathing point
This one surprises people and is worth explaining rather than asserting.
The muscles at the side of the neck assist breathing. If you habitually breathe high in the chest — common with stress, and with any long-standing pain — those muscles work far more than they were designed to, and they sit directly beside the space in question.
Retraining breathing to use the diaphragm reduces that load. It is unglamorous, free, and one of the few places where the stress-and-tension story has a specific mechanical consequence rather than a vague one.

Where acupuncture and massage fit
On the muscles around the outlet rather than on the outlet itself. Tension in the neck and chest muscles that border that corridor is a plausible target, and easing it can reduce symptoms while the strengthening does the structural work.
Condition-specific trial evidence is limited, so that is a reasoned position rather than an evidenced one, and we would describe it that way.
When to see a doctor
Seek urgent care for sudden arm swelling, discolouration, coldness or a weak pulse. See a doctor for progressive weakness or muscle wasting in the hand, for symptoms in both arms, for symptoms following a collarbone injury, or for arm symptoms that have not improved after eight to twelve weeks of proper rehabilitation.
Booking a session in Beverly
Acupuncture is $75 a session and massage is $45 for 30 minutes, $75 for 60 and $105 for 90 — all on our rates page.
See also massage for neck and shoulder pain and desk setup and neck pain. Browse all our articles or get in touch.
Frequently asked questions
What is thoracic outlet syndrome?
Compression of the nerves or blood vessels passing through the narrow space between the collarbone and the first rib. The great majority of cases involve the nerves rather than the vessels, and produce aching, heaviness and tingling in the arm.
How is it different from carpal tunnel?
Carpal tunnel affects the thumb side of the hand, spares the little finger, and is worst at night. Thoracic outlet symptoms tend to involve the whole arm, favour the ring and little finger, and are provoked by holding the arms up or carrying.
What makes it worse?
Sustained arm elevation above all — working overhead, blow-drying hair, reaching for a high shelf, holding a phone to your ear. Carrying a heavy bag on one shoulder is the other common provoker.
When is it urgent?
Sudden swelling, blueness or coldness of one arm needs urgent assessment. Those suggest the vein or artery is involved rather than the nerves, which is uncommon but genuinely time-critical.
How is it treated?
Conservatively in most cases: shoulder blade strengthening, breathing pattern work, and removing the provoking loads. Surgery is reserved for the vascular forms and for nerve symptoms that genuinely fail proper rehabilitation.
This article is general information, not medical advice. Acupuncture is intended to work alongside the care of your doctor, not to replace it. Please speak to a clinician about any new, severe or changing symptom.